




Depression theories are explanations of how biological processes, thinking patterns, learning and life circumstances may contribute to depression. They describe different parts of a complex condition, so the most useful question is which part a theory explains—and whether its evidence supports the conclusion being drawn.
Why can several depression theories be useful at once?
A biological explanation and a psychological explanation need not compete. One describes processes in a nervous system; another describes how a person interprets an experience or changes their behaviour. The mistake is to assume that a useful account at one level must replace every other account. A complete explanation would also need to account for why symptoms differ, why episodes develop at particular times and why the same treatment does not help everyone equally.
Consider the sentence “depression runs in the family.” It may identify a relevant vulnerability, but it does not explain the timing of a particular episode. Conversely, “symptoms began after a job loss” describes a sequence without showing why that person became ill while someone else facing a similar loss did not. These statements can belong in the same explanation, provided their different jobs remain clear.
For a first comparison, separate the question a theory asks from the conclusion readers sometimes add to it. A theory can identify a possible pathway without establishing that pathway in a particular person. It can also suggest a useful treatment target without identifying the original cause. Keep those distinctions in view as you move through the models below.
| Perspective | What it investigates | What it does not establish |
|---|---|---|
| Biological | How inherited differences, neural signalling and other bodily processes relate to depression. The explanation needs to specify which process is being investigated. | A measurable chemical shortage in every affected person, or a personal cause inferred from symptoms alone. Biological involvement does not make circumstances irrelevant. |
| Cognitive | How interpretations, expectations and beliefs interact with emotion and behaviour. Attention goes to the meaning attached to an event. | That all painful thoughts are mistaken, that thinking is the sole cause of depression, or that a person is responsible for becoming ill. |
| Behavioural | How activity, avoidance, consequences and opportunities for meaningful participation may interact over time. A sequence matters more than a character label. | That inactivity originally caused the illness, that every avoided activity is safe to resume, or that simply staying busy is treatment. |
| Learned helplessness and control | How the presence or absence of controllability relates to passive responses in experimental models; how later research revises an earlier account. | That an animal model explains every human symptom, or that a person facing real constraints can change outcomes through effort alone. |
| Psychodynamic and interpersonal | How loss, self-criticism, relationships and changes in roles may be understood or addressed. These approaches have different emphases and are not identical. | That a particular childhood event or unconscious conflict has been established as the universal cause, or that practical adversity is merely a relationship pattern. |
| Stress-vulnerability | How susceptibility and circumstances may interact. This framework connects background vulnerability with context rather than insisting that either works alone. | A personal resilience score, a fixed threshold predicting an episode, or proof that someone with fewer visible pressures cannot have depression. |
Biological models: processes, rather than a missing ingredient
Biological models investigate inherited susceptibility, neural signalling and other processes involved in mood and behaviour. These models are not interchangeable with the claim that every person with depression has a measurable shortage of one chemical. A biological explanation has to specify the process, the evidence and its limits; naming a neurotransmitter is not a complete account of an illness.
The National Institute of Mental Health’s explanation of depression describes contributions from genetic, biological, environmental and psychological factors. That broad account is useful orientation, not a recipe assigning each person a fixed proportion of each cause. Someone’s symptoms cannot be divided into biological and psychological percentages by reading an article or answering a few questions.
Genetic research illustrates both the progress and the boundary. A large genome-wide study of major depression identified hundreds of associated genetic signals. This supports a complex inherited contribution; it does not identify a single depression gene or provide a personal explanation for an episode. An association discovered across a large population is a starting point for investigating mechanisms, not an individual diagnosis.

Cognitive models: the meaning assigned to an event
Cognitive models focus on how interpretations, expectations and beliefs relate to emotion and behaviour. Beck’s cognitive triad is commonly described in terms of negative views of the self, the world and the future. Its value is to direct attention to patterns that may keep distress going, rather than to classify people as simply positive or negative thinkers.
An illustrative example makes the distinction concrete. A person receives a brief reply to a work question. “The reply was short” describes an observation; “everyone thinks I am incompetent” adds an interpretation and a much wider claim. Examining that extra step can be useful even when the workplace genuinely has problems. Accurate cognitive work does not require pretending that unfairness, loss or practical constraints are imaginary.
The error is to turn this model into blame: “You caused depression by thinking wrongly.” A modifiable interpretation is not proof of personal responsibility for an illness. Nor does identifying one harsh thought establish that it was the first cause. Readers who want the treatment approach rather than the explanatory model can move to the guide to cognitive behavioural therapy for depression.
Behavioural models: what happens between activity and mood
Behavioural accounts examine the relationship between actions, consequences and opportunities for meaningful or rewarding activity. Suppose someone stops a familiar group activity because they are exhausted. The immediate result may be relief from effort; a later result may be fewer opportunities for connection or satisfaction. This describes a possible maintaining process. It does not establish that withdrawing was irrational, voluntary or the original cause of depression.
The practical distinction from a cognitive account is the target of attention. One asks what a person believes an event means; the other asks what happens before and after an action. Both can be relevant in the same situation. A useful formulation names the sequence rather than attaching a label such as laziness, because a label does not explain what makes participation difficult or what change would be feasible.

Learned helplessness: an influential model that changed
Learned helplessness is often reduced to the claim that repeated failure teaches a person to give up. That shorthand leaves out a major revision. In their reassessment of learned helplessness, Maier and Seligman describe evidence from animal research that prolonged aversive stimulation can produce default passivity, while learning control can inhibit that response. The mechanism is more specific than the popular slogan.
This research matters because it directs attention to controllability. It also shows why theories should be revisable. However, an experimental model of passivity does not capture every feature of human depression, and its mechanisms cannot simply be read off a person’s behaviour. Someone who is struggling to act may be tired, frightened, constrained, ill or facing several of those difficulties together.
Use the model to ask a narrower question: does this situation offer any genuine, accessible control? Do not use it to demand effort where there is no safe choice. A person facing an abusive environment does not need a lesson that their attitude determines the outcome. Any practical response has to respect the actual conditions, available support and limits on what that person can change.
Psychodynamic and interpersonal accounts: relationships and meaning
Psychodynamic accounts examine themes such as loss, self-criticism, attachment and recurring relationship patterns. Freud’s historical account of mourning and melancholia helped shape this tradition, but it should not be presented as a verified universal explanation that depression is anger turned inward. Historical influence and evidential support are separate questions. A compelling story about the past still needs careful evaluation.
Interpersonal approaches place particular attention on current relationship difficulties and changes in social roles. Their focus differs from attempting to discover an unconscious cause, even though both may discuss loss and relationships. The useful distinction is what the approach asks the person and practitioner to work on, rather than whether the name sounds more scientific or more emotionally meaningful.
These accounts can supply language for a difficult experience without proving a single hidden cause. For example, becoming a caregiver might involve grief over an altered relationship, conflict over responsibilities and reduced opportunity for ordinary activities. Those are distinct pressures. Collapsing them into one personality explanation can obscure practical help, while ignoring their emotional meaning can leave an equally incomplete account.
Is it a risk factor, an episode trigger or a maintaining process?
These three roles answer different questions. A risk factor concerns the likelihood of developing a problem. A trigger refers to something that appears to precede or precipitate an episode. A maintaining process is something that may keep symptoms or difficulties going after they have begun. One factor can play more than one role, but the roles should not be assumed to be identical.
Family history is a useful example of risk without certainty. MedlinePlus Genetics explains the complex inheritance of depression: having an affected relative can increase risk, but many relatives never develop the condition and many affected people have no known family history. The family connection therefore belongs in a probabilistic account. It cannot settle what will happen to a particular person.
Now consider an illustrative episode after a move to a new city. The move may have disrupted familiar support and routines. That timing makes the transition relevant, but a timeline alone does not establish everything that caused the episode. If symptoms persist after the move is complete, it is reasonable to investigate current difficulties rather than insisting that the original event must still explain every day’s experience.

Why the distinction changes a practical response
An explanation of vulnerability may improve understanding while offering little that can be changed immediately. A maintaining difficulty may offer an accessible target even when the original vulnerability remains uncertain. This is why asking “what is making life harder now?” can lead somewhere useful without answering the much larger question “why did this happen to me?” The questions are compatible, but they do different work.
Imagine a person who has stopped joining a regular cooking group because transport is unavailable. A purely motivational explanation misses the immediate obstacle. In this example, arranging access could restore an opportunity; it would not demonstrate that transport caused depression or that returning to the group will resolve it. The practical judgment is modest: address a verified barrier before attributing the difficulty to a psychological trait.
The same care applies when circumstances remain adverse. An individual cannot think their way into secure housing or make an employer provide predictable hours. Psychological support may still be valuable, but it should not be framed as a substitute for changing a material condition where change is possible. A multi-level explanation is useful only if it preserves those concrete differences.
A worked formulation, with uncertainty left visible
Consider an illustrative adult who has a family history of depression, becomes unwell during a period of caregiving and later finds ordinary social activity difficult. A cautious formulation might identify inherited susceptibility as one possible background contribution, caregiving demands as a relevant context and reduced social opportunity as a possible maintaining difficulty. Each part remains a hypothesis about its particular role rather than a confirmed personal mechanism.
Notice what this formulation does not say. It does not allocate percentages, diagnose a neurotransmitter deficiency or decide that the person’s beliefs created the illness. It also does not require one explanation to win. Its value is organisational: different questions become visible, so a discussion can distinguish medical assessment, practical support, relationship pressures and treatment preferences instead of blending them into a single vague cause.
An explanation becomes less useful when it cannot accommodate new information. Suppose the person had also experienced periods of unusually elevated mood, markedly reduced need for sleep and uncharacteristic impulsivity. That history would change the assessment question; it should not be absorbed into a preferred theory without scrutiny. The guide to unipolar and bipolar depression explains why that distinction matters.
What would count as evidence for a depression theory?
A persuasive explanation needs more than a recognisable story. Ask whether the proposed relationship was measured, whether the sequence is clear and whether alternative explanations were considered. These questions do not require a statistics qualification. They require keeping the claim close to what was actually observed, especially when a headline moves from “associated with” to “causes.”
An association tells us that two measured features vary together in the studied data. It does not, by itself, establish which feature came first or whether another factor helps explain both. A study following people over time can clarify the sequence, but being earlier is not enough to prove causation. The design, measurements, comparison groups and remaining uncertainties still matter.

Group findings do not identify an individual’s cause
Suppose a study reports an average difference between a depression group and a comparison group. Even if that difference is reliable, the groups may overlap substantially. The average does not tell you where a particular person falls, whether the finding explains their symptoms or whether changing the measured feature would help them. Those require additional evidence, not a stronger headline.
Symptom diversity makes this especially relevant. In an analysis of STAR*D symptom patterns, researchers found many different symptom profiles among people in a depression treatment study. This does not prove a particular competing theory. It demonstrates why treating everyone with the diagnostic label as though they have an identical presentation can hide clinically meaningful differences.
For a reader, the useful response is to inspect scope. Was the study about adults or children, a first episode or treatment-resistant illness, a laboratory task or daily functioning? A result may be valuable within its actual scope and still be a poor basis for a wider personal claim. “Not established for me” is different from “the research is worthless.”
The chemical-imbalance example
The claim that depression is caused by low serotonin is stronger than saying serotonin signalling is relevant to mood or is affected by some treatments. A widely discussed umbrella review of the serotonin hypothesis did not find consistent support for the simple low-serotonin account across its reviewed evidence. That conclusion concerns a particular causal hypothesis; it does not establish that depression has no biological basis.
It also does not answer the separate clinical question of whether an antidepressant can benefit a particular person. Evidence about treatment outcomes and evidence about the initial cause are different. A medicine can affect a system without proving that the illness began as a deficiency in that system. Equally, an incomplete account of origin does not erase observed benefit or side effects.
Avoid replacing one absolute statement with another. “All depression is a chemical imbalance” and “brain chemistry has nothing to do with depression” both claim more than this evidence allows. The more accurate position leaves room for biological research while rejecting an overly simple personal explanation. Detailed signalling belongs in the separate guide to neurotransmitters and depression, rather than a search for a missing-chemical label here.
A promising subgroup result is not a general treatment rule
Inflammation provides another useful example of the distance between a plausible mechanism and a treatment recommendation. In a small randomised trial of infliximab for treatment-resistant depression, the treatment did not show an overall advantage over placebo on the main symptom comparison. Exploratory findings involving baseline inflammatory markers suggested questions for further research, not a universal remedy.
The reasoning error would be to select the most encouraging subgroup sentence and omit the overall result, sample size and exploratory nature of the analysis. A narrower signal can deserve investigation without being ready to guide routine treatment. Readers should also distinguish a marker measured in blood from a complete account of what is happening in the brain. Related measurements are not automatically interchangeable.
For this kind of claim, ask what would have to be demonstrated next. Would a new study need to confirm the subgroup, specify who qualifies, compare benefits with harms and show a result that matters in daily life? Stating those missing links is more informative than calling an idea either a breakthrough or a failure. Research can advance while a personal treatment recommendation remains unjustified.
How should theories influence treatment and everyday decisions?
Use a theory to organise useful questions, then use clinical evidence and individual circumstances to judge care. A model’s apparent fit is not sufficient to select a medicine, stop an existing treatment or diagnose the reason for symptoms. The approach that tells the most satisfying origin story is not necessarily the approach with the strongest evidence or the best fit for the person’s present needs.
NICE’s guidance on depression in adults describes several psychological and other treatment options, with choice guided by clinical needs and preferences. Behavioural activation focuses on links between activity and mood; CBT addresses interactions among thoughts, feelings and behaviour. This is a reason to compare what treatment involves, not to assign people to simplistic biological or psychological types.

Treatment response is information, not a retrospective diagnosis
If a person benefits from behavioural activation, that benefit supports continuing to evaluate whether the approach is helpful and manageable. It does not establish that reduced activity was their sole original cause. If a medicine helps, the same distinction applies. What changed during treatment can inform the next decision without rewriting the entire history of how the problem began.
Non-response is also easy to overinterpret. “This approach did not help me” is a significant observation, but it is not equivalent to “this model is false for everyone” or “nothing will help.” A useful review asks which outcome was expected, whether the approach was actually accessible and what difficulties remain. Those questions support an informed reassessment rather than a judgement about the person’s effort or worth.
Be cautious when someone offers a complete causal explanation after one questionnaire, one scan image or one laboratory result. Ask what the method has been validated to determine, in which population and with what limits. A legitimate investigation may answer an important narrower question. The problem arises when the explanation expands beyond that question and begins to promise certainty that the evidence does not provide.
Read one claim in three passes
You can practise evaluating a depression claim without logging symptoms, completing a worksheet or deciding your personal cause. Choose one sentence from an article, advertisement or conversation. Read it for its relationship first, its evidence second and its proposed action third. This is a reading method, not a diagnostic exercise or a substitute for treatment.
- Relationship: identify the main verb. “Associated with,” “predicts,” “causes” and “helps” make different claims. Say which relationship the sentence actually proposes before judging its confidence.
- Evidence: identify what was studied. Look for the participants, comparison and measured outcome; distinguish an observation from a treatment trial or a personal story.
- Action: inspect the recommendation. Ask whether the proposed purchase, treatment or change follows from those findings, or whether the advice has moved beyond what the evidence establishes.

For example, consider the illustrative claim “people who stop enjoyable activities become depressed, so resuming any hobby cures depression.” The first clause proposes a relationship; the second turns it into an unrestricted causal and treatment promise. The missing information includes timing, other explanations, who was studied and what treatment outcome was measured. Recognising those gaps is a successful reading result even if you cannot resolve them yourself.
A common mistake is to demand a perfect study before accepting any useful information. That is not the aim. The correction is to match confidence to the question: a preliminary association may justify curiosity, a well-supported treatment result may justify a clinical discussion, and neither necessarily establishes an individual cause. If technical language is tiring, start with one verb—such as causes, predicts or helps—and ask whether the evidence matches it.
Make the next question specific
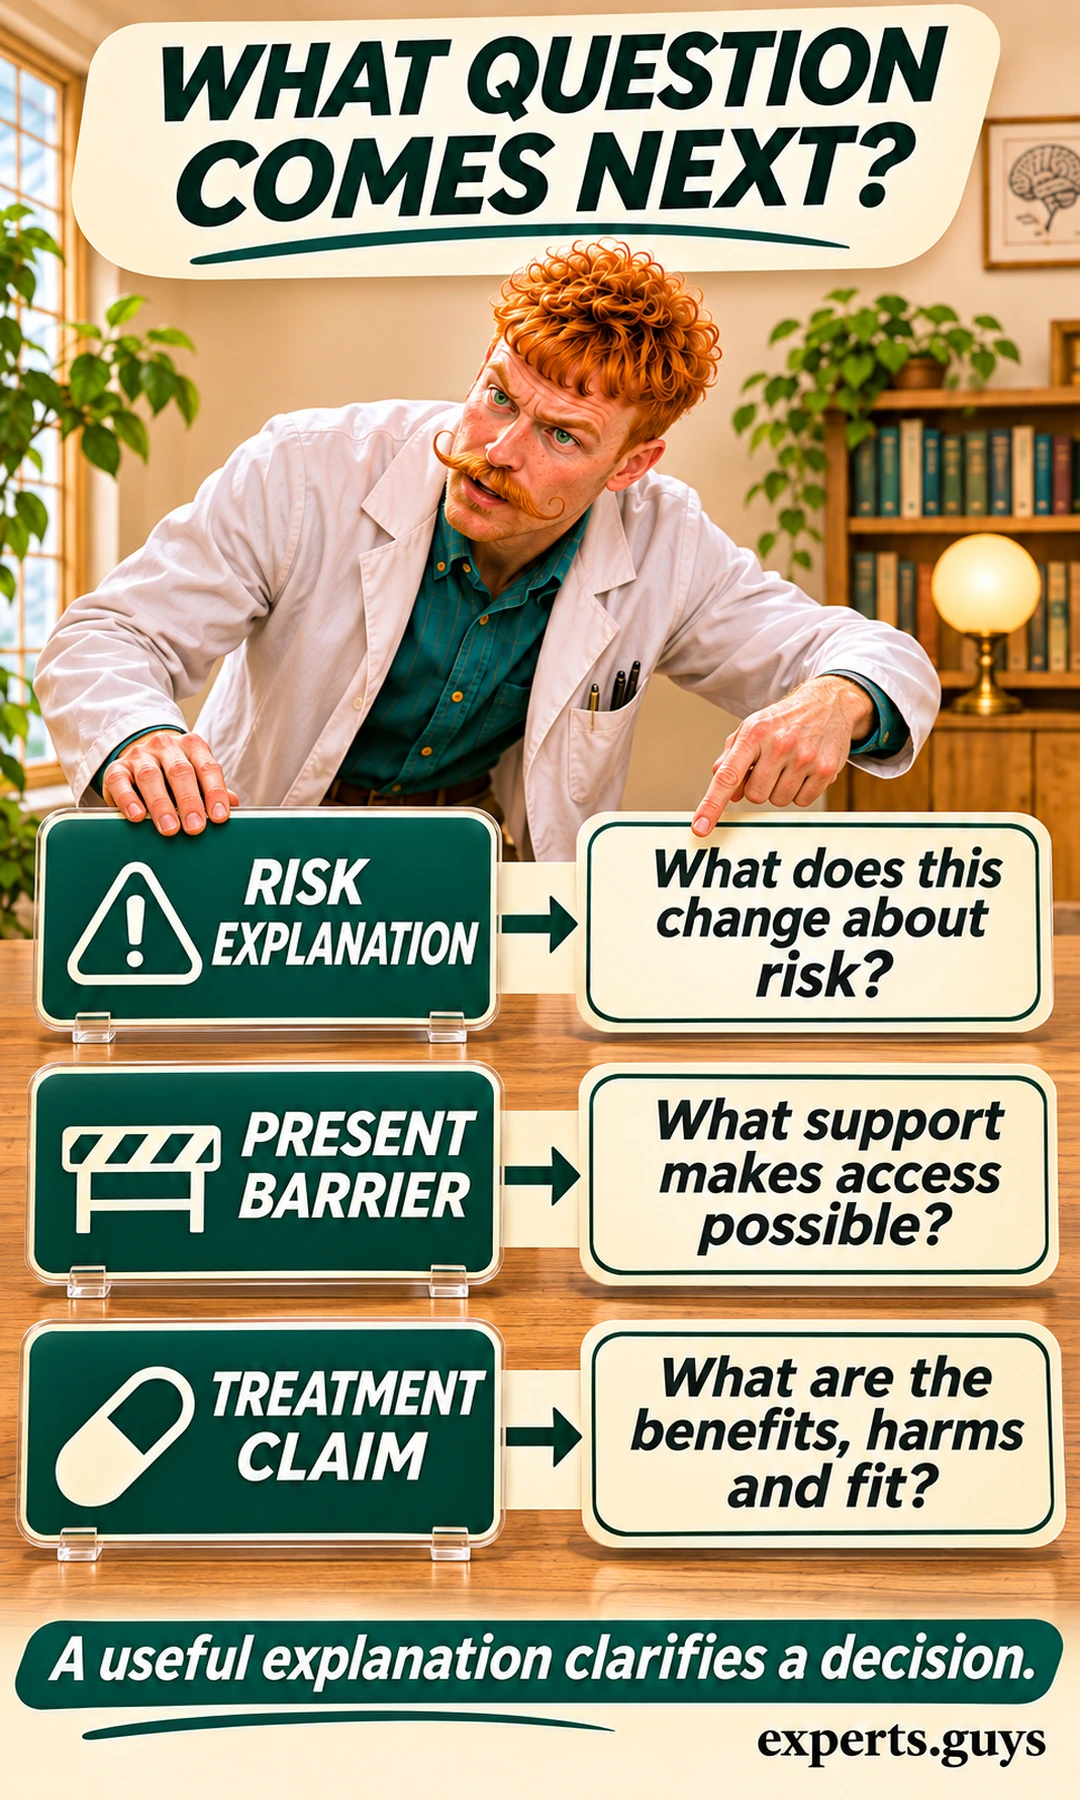
An explanation earns its place when it clarifies the next question. If an article discusses genetic susceptibility, ask what it changes about understanding risk. If it discusses a maintaining pattern, ask what that pattern would look like in practice and what else could explain it. If it proposes a treatment, ask for evidence about benefits, harms and suitability rather than accepting a mechanism as sufficient proof.
| If the explanation concerns… | Ask this next | Avoid this leap |
|---|---|---|
| Background risk | What kind of risk does the evidence describe, and how much uncertainty remains for an individual? A population finding may improve understanding without predicting a personal outcome. | Treating susceptibility as destiny or assuming that a relative’s experience determines your own. |
| A present practical barrier | What support would make the specific activity accessible? Check whether transport, cost, time, safety or another concrete condition is the actual obstacle. | Calling an inaccessible activity a motivation problem, or promising that removing one barrier resolves the illness. |
| A treatment proposal | What outcomes, burdens and possible harms have been studied, and for whom? Separate the proposed mechanism from evidence that the treatment is suitable. | Selecting or stopping a treatment because one explanatory story feels convincing. |
| An unexpected new detail | Does this information change the assessment question or show that the current explanation is incomplete? A useful model must allow revision. | Forcing every new experience into the same theory or postponing assessment until the story feels complete. |
Some questions need assessment rather than a theory debate. Depression-like symptoms can occur alongside medical conditions or medication effects, and a history of mood elevation can change the clinical picture. Persistent difficulty functioning, marked changes in sleep or behaviour, or severe symptoms deserve timely assessment. An explanation should help communicate the problem, not become a reason to postpone appropriate care while searching for certainty.
If there is an immediate risk of self-harm or an inability to stay safe, seek urgent local emergency help and involve a trusted person where possible. That situation takes priority over identifying which model seems most convincing. The purpose of understanding depression theories is to make reasoning clearer and care conversations more useful, while leaving space for uncertainty and the person’s actual circumstances.
Questions about using depression theories
Can a theory still be useful if I cannot identify an obvious trigger?
Yes. An obvious event is not required for an explanation to be useful, and the absence of one does not make symptoms less real. A model may help organise questions about present difficulties or treatment without reconstructing a definite starting point. Avoid pressuring yourself to invent a cause just to make a theory fit.
Does the word theory mean the explanation is only a guess?
No. A scientific theory is an explanatory framework that should be assessed through its specific claims and supporting evidence. However, calling something a theory does not guarantee that all its claims are equally well supported. Ask what it explains, what it predicts and what findings would challenge it rather than judging by the label alone.
Can two people with similar depression symptoms need different kinds of support?
They can have different circumstances, preferences, medical histories and practical barriers even when their symptoms look similar. Those differences matter when considering support. A shared symptom does not establish an identical cause, and a different response to treatment does not show that one person’s experience is less genuine.
Should a family explanation make me seek a genetic test for depression?
A family pattern is not, by itself, a reason to assume that a genetic test will establish your personal cause. Depression has complex inheritance, and a risk association is different from a validated diagnostic result. If a test is proposed, ask exactly what it can determine and whether that result would change an appropriate care decision.
How can I question an explanation without dismissing someone’s experience?
Separate the person’s experience from the causal claim. You can accept that an event was painful, that symptoms are real and that a particular support felt helpful while remaining uncertain about the mechanism. A useful response is to ask what the explanation helps clarify and what it leaves unresolved, rather than treating uncertainty as disbelief.
What if a theory sounds personally convincing but its treatment is hard to access?
Personal resonance and practical access are separate considerations. Ask what the approach actually involves, what evidence supports it and which barriers prevent participation. A compelling explanation should not pressure you to buy an expensive service or accept an unsuitable format. The next discussion can focus on accessible options without declaring one theory the only route forward.
A useful explanation leaves room for the person
The strongest practical starting point is to separate what may increase vulnerability, what happened around onset and what is making life difficult now. Those questions can reveal different kinds of help without forcing a single cause. Prefer explanations that state their limits, accommodate new information and connect to a specific useful decision; be wary of any account that turns uncertainty into blame or a guaranteed cure.










