




Cognitive behavioral therapy (CBT), behavioral activation (BA) and interpersonal therapy (IPT) are established psychotherapy options for depression, alongside approaches such as counseling and short-term psychodynamic therapy. The useful choice depends on your symptoms, treatment history, preferences and what you want to change in daily life. Start by comparing the work you would do in sessions, then ask a qualified clinician how that approach fits your situation.
Psychotherapy is treatment through a structured therapeutic relationship, with methods for understanding or changing difficult thoughts, emotions, behavior or relationships. An appointment may involve discussion, practice, feedback or agreed activities between sessions. A good explanation of the plan should tell you both what happens and why it is relevant to your depression.
This guide is for adults comparing care for depression; it is not a diagnostic test or a way to prescribe your own treatment. Children, adolescents, people with possible bipolar disorder and people with psychotic symptoms need assessment suited to those circumstances. Tell the clinician about previous periods of unusually high energy with little sleep, medications, alcohol or drug use, and earlier treatment responses.
A therapy name describes an approach, while words such as online, individual and group describe how care is delivered. The same approach can be offered in more than one format, and a therapist may combine methods for a clear reason. Use the comparison below to start a discussion, rather than assuming that one matching concern automatically identifies the best therapy.
| Approach | What sessions focus on | A useful question |
|---|---|---|
| CBT | Links between thoughts, feelings and behavior | How will we test ideas and practice changes? |
| Behavioral activation | Avoidance and reduced engagement in meaningful activity | How will activities be paced to my energy and circumstances? |
| IPT | Relationships, grief, conflict or changing roles | Which interpersonal difficulty would treatment focus on? |
| Short-term psychodynamic therapy | Emotions and recurring relationship patterns | How will insight connect to change in my current life? |
| Counseling for depression | Understanding feelings and personal meaning | What depression-specific training and approach do you use? |
| Behavioral couples therapy | Interactions involving a partner | Would joint sessions be appropriate and safe for us? |
| MBCT | Mindfulness and cognitive skills, especially in relapse prevention | Is this intended for current symptoms, relapse prevention, or both? |
Which approach changes what happens in a session?
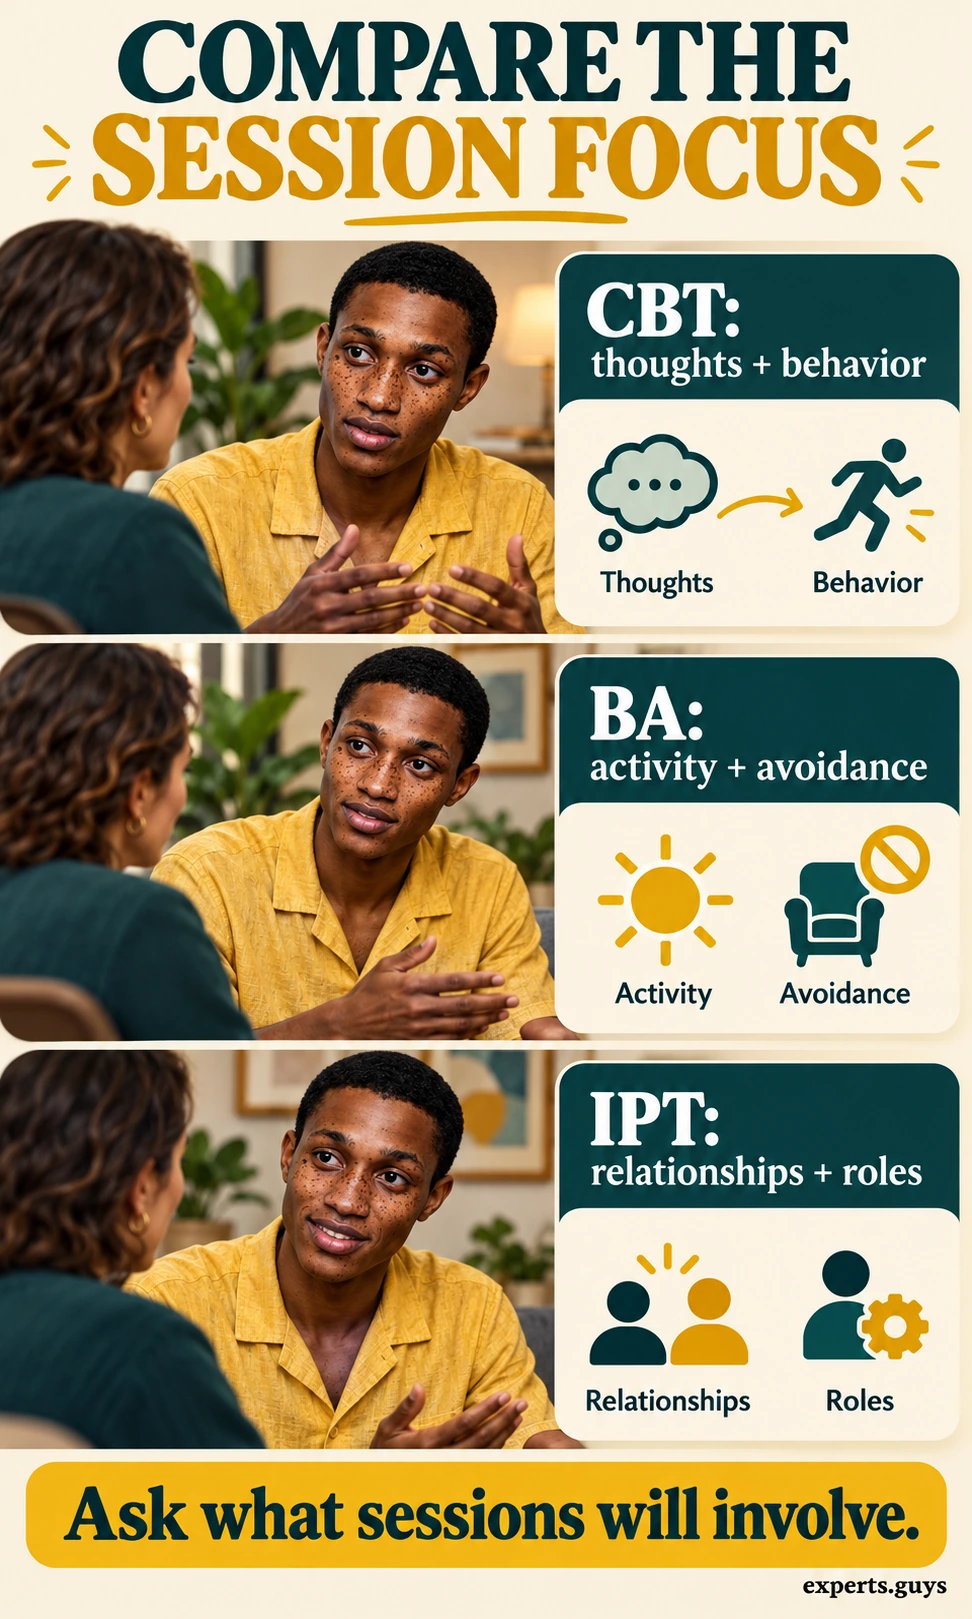
The most helpful comparison is the focus of the work, not the number of therapy names on a provider profile. CBT, BA and IPT offer different ways to organize treatment, although their practical work can overlap. Ask the therapist to explain one likely session using an ordinary situation from your life.
Compare CBT, behavioral activation and IPT
CBT examines how interpretations and actions interact with distress, and it can include trying out different responses. BA puts particular emphasis on the relationship between avoidance, activity and mood, while IPT focuses on current interpersonal difficulties. None of these descriptions means that depression is your fault or that changing an attitude is all the treatment you need.
- Choose one example: “I see a friend’s message, assume I will be poor company, and leave it unanswered.” Say this aloud or keep it as a short private phone note.
- Ask about the focus: A CBT discussion might examine the prediction and response; BA might examine the withdrawal pattern; IPT might explore the relationship or a recent role change. These are illustrations, not a diagnosis.
- Ask about the work: “What would we do in sessions, what might I practice, and how would we know it is helping?” Compare the clarity of the answers.
A common mistake is choosing CBT because it sounds like positive thinking, or rejecting BA because it sounds like a generic instruction to exercise. Ask for a concrete explanation instead of accepting a slogan. If concentration is limited, request one short spoken example; the useful checkpoint is whether you understand the proposed work well enough to discuss it.
A separate guide explains behavioral activation for depression in more detail. This comparison page stays focused on selecting treatment, rather than repeating a full activity exercise. If a provider suggests BA, use that deeper explanation to ask how the approach would be adapted to your circumstances.
Compare insight, emotional exploration and couples work
Short-term psychodynamic therapy explores emotional and relationship patterns, including patterns that may be difficult to notice unaided. Counseling can provide a focused space to understand feelings and difficulties, but the term covers different training and methods. Behavioral couples therapy involves a partner when relationship interactions are relevant to depression and joint work is appropriate.
- Ask for the treatment target: Is the work mainly about recurring patterns, understanding emotions, or changing interactions together?
- Ask for a current-life connection: “How would talking about this help with what I am struggling with now?”
- Check fit and safety: Ask how progress is reviewed and, for couples work, whether private assessment is available before joint sessions.
Do not assume that a comfortable conversation and a depression treatment plan are interchangeable. You can value emotional support while asking what the therapeutic work is intended to change. If there is coercion, intimidation or violence, raise this privately with a clinician or specialist support service; a joint appointment is not the first step for disclosing danger.

Other names require context rather than automatic ranking: ACT, DBT, EMDR, narrative and creative approaches are not interchangeable treatments. For example, EMDR has an established role in PTSD treatment, which is a different question from choosing a routine depression treatment. Ask what condition a proposed method targets, what evidence supports that use and whether it supplements or replaces the main depression plan.
How do treatment phase and delivery format change the choice?
Treating an active episode and reducing the risk of another episode are related but different goals. The appropriate plan also depends on severity, previous response, access and preference, and may include medication alongside psychotherapy. A convenient format matters, but it should still deliver an appropriate method with enough clinical support.
Check whether the goal is improvement or relapse prevention
Mindfulness-based cognitive therapy combines mindfulness practice with elements of cognitive therapy and has a recognized role in relapse prevention. A clinician may discuss it after improvement, especially when depression has returned before. That does not mean a mindfulness app is equivalent to MBCT, or that choosing a course is a reason to stop medication.
- Describe the present situation: Are symptoms currently disrupting daily life, or are you feeling better and worried about another episode?
- Bring the treatment history: Explain what helped before, what did not, and what was difficult to continue. A spoken account or a private phone summary is enough to begin.
- Confirm the purpose: Ask, “What is this course intended to do at this stage, and what is the plan if symptoms worsen?”
The mistake to avoid is choosing a maintenance course solely because it sounds gentler when current symptoms need more support. If you cannot clearly describe your treatment history, start with the most recent episode and let the clinician help reconstruct it. The checkpoint is an agreed treatment goal, not a promise that a particular course will prevent every relapse.

The NICE relapse-prevention quality statement describes psychological therapy options for adults at increased risk of relapse. If repetitive thinking is your main concern, the separate explanation of depressive rumination and overthinking can help you name that experience during assessment. Rumination alone does not decide whether MBCT, CBT or another approach is the right fit.
Choose a format you can realistically attend
Video therapy, an individual office appointment and a therapist-led group are delivery choices, not three separate treatment mechanisms. Guided digital self-help also differs from an unsupported wellness app because a practitioner can help with the structured work. Ask who provides support, how often contact happens and what to do between appointments if difficulties increase.
- Video: Check private space, sound, connection and a backup contact route before committing. Ask whether the provider can legally treat someone in your location.
- In person: Check travel, accessibility, session times and what happens if you cannot attend.
- Group: Ask about the method, facilitator qualifications, confidentiality expectations and how much sharing is expected.
- Guided digital care: Confirm the actual clinician support and escalation route, not just the app’s feature list.
A practical mistake is choosing the easiest appointment slot without checking whether the setting allows you to speak honestly. If home is not private, ask about a suitable in-person option or another supported format instead of trying to manage a session within earshot of others. Choose a format you can use consistently, then revisit it if access itself becomes a barrier.

How can you check a provider and prepare for the first session?
Check professional standing and relevant experience before making a commitment, then use the first appointment to understand the proposed plan. Titles, registration rules and service routes differ between countries, so a qualification should be checked against the relevant local system. A polished website or a long list of therapy abbreviations cannot establish competence on its own.
Verify a provider before booking
- Check identity and registration: Ask for the professional title and registration or license details, then look for an exact match on the relevant official register where applicable.
- Check relevant skills: Ask about training in the proposed approach and experience treating depression in your age group and circumstances.
- Check access: Confirm the full fee, expected appointment frequency, insurance terms where relevant, cancellation charges and likely waiting time.
- Check safeguards: Ask about confidentiality, its limits, and how to obtain help if your condition worsens between sessions.
For example, a person in Austin comparing two therapists could verify their Texas license details before comparing depression experience and appointment costs. That is an illustration of the checking process, not a recommendation for a specific provider. If a public directory is confusing, ask the provider to identify the regulator and explain how you can independently check their standing.
Do not substitute star ratings for the verification step, and do not assume a short introductory call is a clinical assessment. Keep the comparison to information that changes your ability to use the service. The broader mental health counseling guide covers the wider support landscape; this page concentrates on matching a depression treatment approach.

Prepare a simple first-session agenda
You do not need a polished life story or completed worksheets before the first appointment. A specific recent difficulty gives the clinician a starting point for questions about symptoms, daily functioning and context. An agenda helps you remember what matters without turning preparation into another overwhelming task.
- Describe one moment: “I opened a friend’s message and could not bring myself to answer.” Add what you noticed, rather than trying to explain the cause.
- Name one goal: “I would like to stay in touch without avoiding every message.” Make it about daily life, not a requirement to feel happy all the time.
- Give relevant context: Mention current treatment, major changes, previous therapy and any immediate safety concern.
- Ask for the plan: “What approach are you proposing, why, and when will we review whether it is helping?”
Use a brief private phone note, a voice memo stored securely, or simply speak from memory. Do not record the therapy session without discussing consent, and avoid putting sensitive details into an unfamiliar app. If preparation becomes exhausting, bring just the one example; the therapist can help organize the rest.

How do you make therapy workable and review progress?
Therapy should have room for feedback about both the work and the relationship. Between-session practice, when part of the approach, needs to be understandable and feasible, while progress reviews should consider symptoms and daily functioning. Neither completing every task nor feeling immediately better after every session is a complete measure of treatment success.
Adapt practice when it is too difficult
- Name the barrier: Say whether the difficulty was fatigue, confusion, time, privacy, distress or a task that did not seem relevant.
- Ask for an adjustment: “Can we rehearse this in the session, reduce the task, or use a spoken rather than written version?”
- Keep the purpose clear: Ask what the smaller version is meant to help you learn or change.
- Review the attempt: At the next contact, describe what happened, including if you could not start.
For example, a long digital practice form might be replaced with one brief observation discussed in the next session, if the therapist agrees that this preserves its purpose. The adjustment is an illustrative conversation strategy, not a substitute treatment protocol. A missed task supplies information about the plan; hiding it makes adaptation harder.
Avoid independently turning a challenging assignment into an entirely different activity while assuming it has the same purpose. Ask for a manageable version and agree what to notice afterward. If practice produces significant or persistent distress, stop that practice and contact the clinician for advice rather than forcing completion.

Review progress with a clear next decision
Agree when the plan will be reviewed and what improvement would look like for you. NICE recommends reviewing how treatment is working between two and four weeks after it starts, but an early review is not a deadline for recovery. The review timing may need to be sooner for safety concerns, deterioration or treatment-specific monitoring.
- Compare with the starting point: Discuss symptoms and the daily-life goal you agreed, using the same examples where possible.
- Describe barriers and unwanted effects: Include attendance problems, distress, difficulty with practice or feeling misunderstood.
- Ask for an interpretation: “Is this the expected course, or does the plan need to change?” A clinician may use a validated symptom measure alongside the conversation.
- Agree the next decision: Continue the plan, adapt the method or format, reassess the diagnosis or discuss additional treatment. Clarify the next review point.
A hypothetical sign of progress might be answering one friend more consistently even while low mood remains. That observation is useful context, but it does not by itself prove that treatment is effective or complete. If you cannot track details, bring one example of what is easier and one of what remains difficult; no spreadsheet or daily score is required.

| What you notice | What to raise at review |
|---|---|
| The plan is unclear | Ask the therapist to explain the treatment target and how sessions connect to it. |
| Tasks repeatedly do not happen | Describe the barrier and request a realistic adaptation. |
| You feel unable to disagree | Discuss the relationship directly if safe, or seek another qualified provider. |
| Little improvement after an agreed treatment period | Ask about reassessment, approach, treatment intensity and other contributing problems. |
| Marked deterioration or new safety concerns | Contact the care team promptly; use urgent or emergency care when needed. |
You can question a treatment plan without deciding that therapy as a whole has failed. Equally, a therapist should not dismiss persistent deterioration as something you must simply endure. Ask how a change would be coordinated, especially if another clinician is prescribing medication, and do not change that medication on your own.
Frequently asked questions
Is there one best psychotherapy for everyone with depression?
No. Evidence, symptom severity, previous treatment, coexisting difficulties, preferences and access all affect the decision. Ask for a clear rationale for the proposed approach rather than a universal ranking.
Does therapy have to involve talking about childhood?
Not necessarily. Some approaches emphasize current difficulties, while others explore how earlier experiences relate to present patterns. Ask how past experiences would be used and why they matter to your treatment goal.
Can psychotherapy be used with antidepressants?
Yes. Psychotherapy and medication may be used together, particularly when depression is more severe or previous care has not been enough. The prescribing clinician should guide medication decisions and coordinate with the therapy plan where appropriate.
Is an AI chatbot the same as psychotherapy?
No. A chatbot does not establish that you are receiving assessment and treatment from a qualified professional. Before using any digital service, check who is responsible for clinical care, how information is handled and what support exists if symptoms worsen.
Can I change therapists if the first match feels wrong?
Yes. You can discuss the problem, ask whether the work can be adapted, or seek another appropriately qualified therapist. If you already have an active care plan, ask how continuity and transfer of relevant information can be handled with your consent.
Choose the next conversation
Start with one treatment approach you want to understand and one practical question about receiving it. Ask a qualified provider what the work involves, why it fits your situation and how the plan will be reviewed. A useful outcome from the first conversation is a clear next step you understand, even if the final treatment choice needs further assessment.
Sources and further reading
- NIMH: Psychotherapies – treatment conversations and questions for providers.
- NICE: Depression in adults, treatment and management – treatment selection and review.
- NHS: Treatment for depression in adults – overview of approaches and combined care.
- NHS: Cognitive behavioral therapy – what CBT involves.
- NHS: Counseling – the counseling process.










